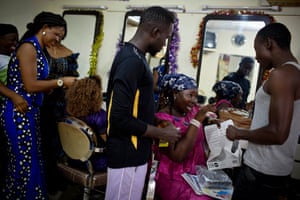Ruth etiketine sahip kayıtlar gösteriliyor. Tüm kayıtları göster

22 Kasım 2016 Salı

How UK trade policies could help heal global healthcare inequalities | Ruth Bergan and Natalie Sharples


Theresa May’s recent visit to India, during which discussions about cooperation over trade in health services were a priority, is a reminder that trade and investment cannot be isolated from other areas of policy.


Key among these is universal health coverage – the provision of quality medical services to all people when they need them, without causing financial hardship. This is a concept that is having its moment: it is championed by everyone from health activists to the World Bank, and is one of the targets in the sustainable development goals.


What is obvious, but perhaps less palatable to some of its advocates, is that achieving universal health coverage requires addressing polices far beyond the health sector. Policies that need to work for universal health coverage include those on water and sanitation, nutrition and education, but also global policies and practices that impede the right to health.


In the context of Brexit, UK trade is one such policy we urgently need to examine. Trade has huge implications for health. This was seen very clearly in the EU’s failed attempt to agree a trade deal with India. When the EU proposed to include stricter patenting rights for companies in the deal, Indian negotiators, the UN and activists all raised serious objections, fearing it would drive a huge increase in the cost of medicines relied on by poor communities across the globe.


Fears about trade rules are well-founded. One third of the world’s population lacks access to essential medicines. New treatments for people living with HIV in middle-income countries can cost between $ 3,000 (£2,400) and $ 28,000 per person each year. No surprise that for many people this is out of reach. Inequalities in power between companies and citizens is at the heart of this. Patent protection given to pharmaceutical companies through provisions in trade agreements restricts access to cheaper, generic medicines and pushes up drug prices. In the US, the Food and Drug Administration reports that the cost of a generic drug is 80% to 85% lower than the brand name product.


Similar power distortions are unmistakable in bilateral investment treaties. Like the controversial TTIP and Ceta agreements, these trade deals include a parallel judicial system allowing companies to sue governments at private international tribunals, curbing the ability of states to provide for the right to health for their people, and undermining democracy.


Companies are already using such provisions to challenge government health policy. In 2012, pharmaceutical giant Eli Lilly began legal proceedings against the Canadian government for $ 500m for invalidating two of its patents. The invalidations were the result of a new national law that required the “utility” of an invention to be demonstrated when the patent was filed – in other words the drug did not do what the inventor said, or implied, it would do when the patent application was made, as was the case with the two contested drugs from Eli Lilly. The company then sued Canada under the Nafta treaty for lost profit and unfair treatment – a lawsuit that is not only intended to challenge the withdrawal of the patents but also Canada’s national law.


While there are no public cases of health companies suing India, UK companies have certainly been using the provisions of UK bilateral investment treaties to challenge other aspects of Indian government policy. Vedanta Mining and Vodafone have both challenged changes to Indian tax law. The companies had used offshore vehicles to buy out Indian companies, neatly avoiding having to pay significant amounts of tax. When India attempted to close the loophole (pdf) that allowed this to happen, the companies used the UK-India treaty to sue the government for “compensation”.


Every day 16,000 children under-five (5.9 million a year) die. The causes of their deaths are largely preventable, meaning these children are not killed by illness, but bad policies. As the Alma Ata – the first international declaration underlining the importance of primary health care – made clear almost 40 years ago, health inequalities within and between countries are “politically, socially and economically unacceptable”. Achieving universal health coverage requires training more health workers, improving health information systems and mobilising more domestic financing. It also requires addressing the global causes of poverty and inequality. Trade and investment policies should be first on the list. India has already revised its bilateral investment treaties to limit the range of policies that can be challenged. The UK now has an opportunity to make sure its own trade policy supports the health of people across the world. We must demand that MPs act now to ensure it.


• Natalie Sharples is senior policy advisor at Health Poverty Action


How UK trade policies could help heal global healthcare inequalities | Ruth Bergan and Natalie Sharples

29 Ağustos 2016 Pazartesi

Giving birth in Guinea: a life or death lottery bereft of midwives and medicine | Ruth Maclean

A baby was born, took one breath, then left the world again. No amount of the midwife pumping his legs up to his ribcage and back, or poking a finger hard and fast at his chest, would bring him back.


His 17-year-old mother lay in pain on the delivery table as her son was wrapped up in a yellow cloth. There was no time even for her to hold him, as another woman was about to give birth. The midwives quickly changed their bloodied robes and gloves. Because there was no other table, the second woman gave birth lying on the floor.


This time, the baby yelled as soon as she came out. She was healthy. While the midwives moved on to the next urgent case, their small delivery room filling up, she spent her first few minutes screaming on the concrete slab.


Welcome to life in Guinea, baby Katherine.


The situation for newborn babies and their mothers in this west African country is dire. Of every 1,000 babies born in Guinea, 123 die before their fifth birthday. For every 100,000 live births, 724 women die. Guinea has the world’s second-highest rate of female genital mutilation (FGM), after Somalia – 97% of women between 15 and 49 have been cut. Women who have had FGM are twice as likely to haemorrhage during childbirth, and haemorrhage is the leading cause of mothers dying in Africa.


Medicine is in short supply, and health workers’ salaries rely on selling enough of it. This leads to staff shortages; most health centres have one or two health workers when they should have eight.


The Ebola outbreak, which killed more than 2,500 people in Guinea, revealed how little access to medical care rural Guineans had. The health situation has improved slightly post-Ebola, but without donor money, the system would grind to a halt.


“The needs are identified, but the money is just not coming from the government,” says Guy Yogo, Unicef’s deputy representative in Guinea. After Ebola, the government increased its contribution to health from 2.66% to 4.66% of GDP, and has committed to 7% for next year. According to Yogo, however: “The minimum is 11-15% if you really want to have an impact.”


Katherine is one of nearly 5,000 babies officially born each year at Doko health centre in the Kankan region of north-eastern Guinea, but about 2,000 more are born to unregistered mothers who come to the area to search for gold in artisanal mines.


Births take place in one small room, with its single delivery table presided over by two midwives.


“Lots of women come, and there’s nowhere to put them all. They often have their babies on the floor. Better there than next to sick people – at least it’s clean,” says Bernadette Mansaré, a midwife.


Sayon Keita, who is pregnant with her seventh child, is examined by a midwife at a health post near Doko, Siguiri


Sayon Keita, who is pregnant with her seventh child, is examined by a midwife at a health post near Doko, Siguiri

When there is a moment between deliveries, she lectures the dozen pregnant women waiting outside on the importance of coming in for checkups.


Doko’s midwives have not had any training in 20 years. If they had, they might have known how to give the baby who died mouth to mouth resuscitation or proper compressions. Thousands of babies die from preventable causes each year.


One of the things that the response to Ebola brought was medical supplies, the like of which had not been seen in a generation.


Kondiadou health centre is near Kissidougou, one of the towns to which the UN started regular flights during Ebola. Before, reaching south-east Guinea from the capital involved a bumpy car journey lasting several days. Now, because of the flights, it is easier to get supplies and staff in, although the UN is expected to cancel the flight as soon as the threat of Ebola is completely over.


“It’s the first time we’ve got equipment like this since the centre was built in 1990,” says Therese Soropogui, a community health worker at Kondiadou, as she pulls out standard latex gloves and yellow washing-up ones and explains the difference.


Why do women still die in childbirth?

A small camping stove, some sterilising kit, bandages and a few hundred pairs of gloves have been donated by the Spanish government and Unicef. And a red plastic bucket. It does not take much to save lives in remote Guinea.


“Before, we burned tools in the fire, and that took too long,” Soropogui says. “And if you had two women giving birth at the same time, you had to use our one set of tools for both women, one after the other. That was very difficult. Now we have three or four sets of tools and, at the end, you can sterilise them.”


Not all of the equipment seems to have been used, however, showing up what many see as an endemic problem with the UN’s approach.


“They give out supplies like sweets,” says Yolande Hyjazi, the country director of Jhpiego, an international health organisation. “The UN system is: what the government asks for, they buy, and that’s it. We’ve seen a lot of vacuum extraction equipment, but if you ask the staff about it they say: ‘I don’t know [what it is], the UNFPA [UN population fund] sent it.’ They give equipment without training.”


Even when staff do know how to use it, obstetric equipment does not solve a problem many women have – getting to a clinic.


Harriet Somadouno, a 20-year-old farmer in her third trimester, walked 17km to Kondiadou for a checkup, carrying 10kg of peanuts on her head to sell at the market en route.


“I walked with my friends, but I carried the peanuts myself,” she says. “It took me six hours. I’m going home tonight but I think it’ll be a quicker journey as I sold all the peanuts – perhaps four hours.”


Somadouno, exhausted after her walk, barely seemed to take in the information given by the nurse.


One scheme to help women involves what looks like a giant old-fashioned pram, which is attached as a sidecar to a motorbike. Spain has given 15 of them to health centres in Guinea.


Mamady Berete doubles up as Doko health centre’s broken bones specialist and the moto-ambulance driver. Dressed in high-vis from head to toe, he bumps up and down bush tracks and through enormous puddles, picking up pregnant women, strapping them in his sidecar and taking them to Doko.


The giant pram turns heads, but brings fresh problems, such as how to pay for petrol or maintenance.


“We have someone here who can fix it but, if a tyre breaks, we have to send to Conakry for a new one. It’s a bit difficult,” Berete says.


On his trips to the villages, Berete spreads the word about the health centre and encourages more people to use it.


Mamady Berete heads off to collect a pregnant woman from a remote outpost


Mamady Berete heads off to collect a pregnant woman from a remote outpost and bring her to the Doko health centre

Trust in Guinea’s health system was in short supply during Ebola, when clinics closed their doors, doctors and nurses died, and infected people seemed to disappear into hospitals never to return.


“People were afraid of our health centre – they said if you came here you’d catch Ebola. So people avoided coming,” says Berete. Because nobody came, salaries could not be paid, so the clinic had to shut, leading to even less trust in the service.


According to Yogo, the lack of working health systems meant the death toll from “collateral” diseases and health complications outpaced that of Ebola.


“More people died from malaria, diarrhoea and in childbirth than of Ebola,” he says. “The country did not have enough ambulances. They were all used for Ebola patients – nobody else.”


Now, people are trying to take advantage of the supplies and attention that Ebola brought, and keep people coming through the doors so staff can afford to keep those doors open.


Berete and his colleagues are succeeding: several health centres, including Doko, are recording pregnant women coming in greater numbers than before Ebola.


Somadouno, who left school aged nine and had her first child at 16, plans to repeat her gruelling 17km journey to give birth.


“I gave birth to my first child here and, because it went well, I’m coming back for this one,” she says. “My mother-in-law will come with me, but we’ll be on foot then too. My plan is to try to catch it early.”


Giving birth in Guinea: a life or death lottery bereft of midwives and medicine | Ruth Maclean

12 Ağustos 2016 Cuma

Guinea eyes official end of polio outbreak but bigger challenge remains for Africa | Ruth Maclean

Life on an informal gold mine is hard for any child. In Guinea, it means searching through piles of dark earth for glittering particles from a young age, going hungry if the family has no luck that day, and surviving violent attacks by other miners or the authorities.


For Lounceny, a dark-eyed boy who has spent the first four years of his life watching his mother look for gold in Kintinian in the country’s north-east, life is harder. He caught polio when he was two.


“It started with a wound on his foot,” says Lounceny’s grandmother, Sita Aidara, touching her frightened grandson’s shoulder as he sits on a wooden bench beside her, trying to keep him calm. “He started complaining about his leg – then it spread to the other one.”


Related: Pakistan and Afghanistan join forces to wipe out polio


She took him to a clinic 20 miles away, where it was confirmed that he had become one of the few children in Africa to contract polio. There was little they could do for him, and now Lounceny cannot walk. His family has to carry him to the mines, where he sits on a mat all day as they search.


On Thursday, Africa was set to celebrate two years with no new cases of wild polio, a major step on the way to consigning cases like Lounceny’s to the past. However, the global fight to eradicate the disease suffered a blow when two new cases were found in Nigeria.


Globally, hundreds of thousands of children used to become paralysed as a result of polio every year, before vaccines were developed in the 1950s and 1960s. While it was almost eliminated in rich countries, the problem endured in poorer states. The Global Polio Eradication Initiative, set up in 1988 by Rotary International, the World Health Organisation (WHO), Unicef and the Centers for Disease Control and Prevention (CDC), has now almost managed to eradicate the disease.


When Nigeria marked two years without any new cases last month, Afghanistan and Pakistan were thought to be the last countries in the world left where polio is endemic. However, Nigeria’s celebrations were premature. The WHO said the strain of polio discovered there is most closely linked to one last seen in Borno in 2011. The two children have become paralysed.


Nigeria’s minister of health, Isaac Adewole, put the latest occurrence down to the “insurgents’ eclipse”, referring to the fact that the terrorist group Boko Haram controlled large swathes of territory in Borno state, where the polio cases were found. Health workers could not get there and vaccinate children for months.


Women pan for gold in the mining area of Siguiri, Guinea


Women pan for gold in the mining area of Siguiri, Guinea. It was in such circumstances that Lounceny contracted polio. Photograph: Kate Holt/Unicef

“Mr President himself, when we had a meeting last week, observed that as we liberate more areas, we should expect challenges,” Adewole told Nigerian media. “But we did not expect that there would be polio. We were expecting nutrition and other problems.


“It wasn’t that we were not doing the job. A chunk of the state was out of reach, and we couldn’t reach children there.”


Nigeria had appeared to be losing the battle against the disease, with some states banning all vaccines in 2003 amid suspicions about their safety. There were also several attacks on people administering vaccines. However, an immunisation campaign led by the CDC vastly improved the situation.


Africa needs three years with no new cases to be declared officially polio-free. The Nigeria outbreak resets the clock.


Guinea, one of the poorest countries in Africa, ranked 182nd out of the 188 countries in the UN’s 2015 human development index, had its last big outbreak of wild polio in 2009, when there were 41 cases.


But a new outbreak of vaccine-derived polio hit in September 2015, after the crippling Ebola outbreak that diverted all Guinea’s healthcare efforts. Seven children under five contracted the virus in the eastern region of Kankan.


“At that moment the Ebola outbreak hit, so we couldn’t do anything,” said Souley Lalibou, leader of the WHO’s polio response in Guinea. “While Ebola was happening, everything else stopped.”


Children sit outside a clinic in a community near Doko, Siguiri, in northern Guinea


Children sit outside a clinic in a community near Doko, Siguiri, in northern Guinea. They have just been vaccinated for polio as part of a Unicef campaign backed by the Spanish government. Photograph: Kate Holt/Unicef

As soon as they could, the WHO, Unicef and the government launched a campaign to stamp it out. In two weeks, Lalibou will find out whether their efforts paid off and Guinea’s polio outbreak is officially over.


“There are probably more cases out there that we don’t know about, but I don’t think there are any wild cases,” Lalibou said.


Vaccine-derived polio is easier to control than wild polio, but the effect on a child’s life is the same.


Lounceny only had one dose of the polio vaccine. Aidara wished she had known the risk to her grandson, as she would have tried to get him the 20 miles to the clinic for his second dose.


“His mother was in the mines, trying to earn money so we could eat. We didn’t know he could get polio,” she said.


As it is, the whole family struggles to survive at the same time as looking after a child with disabilities.


“The problem we have is that if you don’t carry him, he can’t move,” Aidara said. “You always have to help him. Taking care of him and looking for gold don’t go together. I’m really worried about his future – I don’t know what it will be like.”


Guinea eyes official end of polio outbreak but bigger challenge remains for Africa | Ruth Maclean

Conakry hairdressers dispense cut-and-dried contraceptive advice to women | Ruth Maclean

Fatoumatah Bah is cornered. Sitting in front of a tinsel-ringed mirror in Miskaa Salon, her head is bent forward, two women at work braiding twists into her hair. She will be stuck in the chair for at least three hours.


It is a good moment to pounce. Fatoumatah Kamara, 20, an apprentice hairdresser in a matching skirt and blouse and glinting cherry earrings, sidles up to Bah. She starts to make conversation.


At first, it is the usual hairdresser chatter. What rain we’ve been having, eh? Where are you from? What are you up to this weekend? This is the 20-year-old accountancy student’s second visit to the salon in Guinea’s capital, Conakry.


Soon Kamara’s questions become more personal. Does Bah have a husband? A boyfriend? Then she goes in for the kill. Does she know there are ways of avoiding getting pregnant?


With every manicure, pedicure and hairdo at the Miskaa Salon, clients receive a free treatment: a great deal of contraceptive advice.


Related: Contraception and family planning around the world – interactive


Five salons across Conakry have been dispensing family planning advice since 2012, and they have been so successful that the project – the brainchild of Jhpiego, a health organisation associated with Johns Hopkins University in the US – is about to be extended to salons in Guinea’s seven major cities.


In Guinea, which has one of the lowest rates of modern contraceptive use in the world, women have an average of five children. According to UN figures, in 2015 only 7.5% of married or cohabiting women use some form of contraception.


A lot of effort has gone into teaching women in rural Guinea about family planning, but not so much in urban areas. A salon is an excellent place to reach them, so long as it is the right kind of salon.


“It’s better to go where they do braids because that’s what women traditionally want,” says Yolande Hyjazi, Jhpiego’s director in Guinea. “A woman who’s straightening or washing her hair has more money and more access to information.”


Across town from Miskaa, Jumelle Coiffure is trying to turn around clients as fast as possible, largely because the room is impossibly cramped. Jumelle is owned by 32-year-old twins Tata Sylla, wearing a short black and bright green wig, and her sister Mbalia, with long, heavy braids.


“There were a lot of young women getting pregnant around here when they didn’t want to, with lots of kids running after them, and I thought it would be good to teach them how to avoid that. Even my apprentices were getting pregnant,” says Mbalia, making up Aminata Kouma’s face just inside the salon door. Outside, a dozen girls huddle under the dripping overhang of the salon’s tin roof, filing fingernails and tugging at each other’s hair.


An apprentice hairdresser at the Jumelle salon in Conakry shows a client different family planning methods


An apprentice hairdresser at the Jumelle salon in Conakry shows a client different family planning methods. Photograph: Kate Holt

Kouma, 35, says she first heard about family planning at Jumelle.


“I never knew about this before coming here – they taught me how,” she said. “I got the injection, and since then I’ve been able to control the number of children I have. I already have four and I don’t want any more. My husband can’t afford it, school fees are so high. There’s too much suffering here. I’m a housemaid, but I’m out of work.”


Each salon has an army of apprentices, some of whom have worked in them for years, to cope with the intensity of the work and the number of clients. Jhpiego deliberately chose very popular salons to reach as many people as possible, and trained some of their apprentices as community health workers, to explain how to use exclusive breastfeeding to prevent pregnancy, talk about implants, sell pills and write referrals. They earn half the sale price for any pills and condoms they sell.


The trial started in 2013, but everything had to stop for the Ebola outbreak. Like all health organisations, Jhpiego had to turn its efforts to fighting Ebola. In any case, women were not going to the salon.


It is now back in full swing, though, and tailors’ shops are the next target. “There are women that wait around all day for their dresses, trying them on,” Hyjazi said. “People are being social, hanging around. But in the tailors’ shops we also have a lot of young men. Reaching men is important.”


The idea is that clients of both establishments will talk to their friends, and word will spread.


At Miskaa, a large wedding party is getting ready.


Apprentice hairdressers cluster around each client, carefully painting on long, black eyebrows, blow-drying hair straight, and making minute adjustments to towering, shiny headwraps.


Kamara, pointing at her laminated booklet, has just finished explaining how to use a string of beads to track fertility. But it isn’t new to Bah.


“I go on Google, I go on YouTube, I find information,” she says. “But not everybody is a student like me.”


She knew about condoms and pills, but not the other methods Kamara talks about. Young people have far more access to information than previous generations, and sex is slowly becoming something that is more talked about.


Young men who have come to Conakry’s Miskaa Salon for cut price condoms are shown how to use them correctly by apprentice hairdresser Nene Diakité.


Young men who have come to Miskaa Salon for cut price condoms are shown how to use them correctly by apprentice hairdresser Nene Diakité. Photograph: Kate Holt

Traditionally, a Guinean woman would space out her children by leaving her husband and going back to her mother’s house for a few years, every time she had a baby.


“Now no one is using abstinence, so everyone is using contraceptives, but no one is talking about it,” Hyjazi says. “Many people think that if a women is using contraceptives, it’s because she has another partner. There’s not a lot of open communication – even between a husband and wife using them. Many women will use the pill without telling their husbands.”


One thing is unlikely to change, though, and according to Hyjazi, it is skewing the statistics, because people doing surveys do not always do them in private. “If a woman is asked if she’s using contraceptives and her mother or mother-in-law is there, she’ll never say yes.”


The wedding party is almost ready. Kamara looks over each woman carefully before opening the door for them. In a few hours, they have become more glamorous and, thanks to Kamara, more contraceptive-savvy.


“I like making women beautiful – that’s why I work here,” says Kamara, already looking around for her next quarry.


Conakry hairdressers dispense cut-and-dried contraceptive advice to women | Ruth Maclean

11 Nisan 2014 Cuma

Art therapies have turn out to be a mainstream spouse to medicalised healing | Ruth Wishart

woman listening to music on headphones

‘Autistic young children who have an acute sensitivity to sounds apparently reply well to musical loops in which pleasing tracks offer the two a sense of calm and a predictability.’ Photograph: Getty Photographs/Picture Supply


There is a fire extinguisher featured in Bridget Riley’s latest artwork, unveiled earlier this week. Many in fact, provided they are an obligatory element of the furniture in hospital corridors. And the 56 metres of this arresting mural, with characteristic horizontal lines in daring colours, adorn the 10th floor of St Mary’s Hospital in London.


The charity that commissioned it, Imperial School Healthcare, reasons that the influence is therapeutic on personnel as properly as the more transient audience of sufferers. It says high-good quality bold murals will provide distraction in surroundings frequently serially stressful – the ninth floor homes intensive care.


The Riley mural delivers everlasting adornment, but some one,600 artworks owned by the charity now circulate amongst five hospitals in west and north-west London, cautiously curated to reflect their surroundings one paediatric wing demonstrates animated films created by younger individuals encouraged by an artist with a six-month residency.


It is evidence, if any were still necessary, that art therapies have turn out to be a mainstream spouse to medicalised healing rather than a niche practice. There is no lack of empirical proof that the producing and viewing of artwork has developed crucial final results in situations as varied as depression and disability.


Music therapies, also now the topic of a raft of academic assessments, have created some dramatic outcomes. The broadcaster Sally Magnusson has set up a charity in memory of her late mother, Mamie – a vivacious journalist and wife of the late Magnus Magnusson – whose dementia brought memory loss but also, heartbreakingly in a lady for whom phrases and their precise utilization were a passion, an inability to string with each other rational sentences.


But, as her daughters identified, what she could even now do was sing. Sing the well-loved songs of childhood, family members outings and celebrations. Playlist for Life aids equivalent sufferers by loading personalised musical recollections on to an iPod to be played to them by families or carers. It is a pity, notes Sally drily, that between Mamie’s complete recall was each and every track from The Sound of Music, now lodged all also retrievably in her personal memory.


The celebrated neurologist Oliver Sacks wrote extensively about this phenomenon in his 2007 guide Musicophilia: Tales of Music and the Brain. His contention is that where musical recollections are lodged in the brain is near to other locations that dementia or stroke victims are no longer capable to access.


They get rid of, he says, “their autobiography”, their identity, their story but an evocative piece of music, the soundtrack to their earlier existence, can retrieve not just the sounds themselves, but the occasions connected to them. And in so doing it can give the two lethargic and agitated patients hrs of peace and pleasure.


The United kingdom-broad Music in Hospitals motion, which has professional musicians bringing enjoyment to care residences and hospices as well, is clear that its performers must have extremely designed social antennae to match their musical accomplishment. They need to understand and react to varying temperaments and tastes.


Music as a balm for troubled souls has emotional potency. Severely autistic kids who have an acute sensitivity to sounds – which might mean daily noises like vacuum cleaners or phones result in distress – apparently react effectively to musical loops exactly where pleasing tracks provide each a sense of calm and a predictability which several on the autistic spectrum discover comforting.


There is also the healing of wounds of a non-medical origin. When Liverpool’s 2014 Biennial opens on five July, the inaugural concert will feature a Hillsborough Memorial symphony composed by Michael Nyman. No eleven Symphony is primarily based on music he was composing as the tragedy unfolded. It will, undoubtedly, result in a fresh shedding of tears by the households of the 96 victims. But then tears are therapeutic also.


What all this tells us, not least at the moment when breasts are currently being routinely beaten above drug budgets, is that what have been sometimes pejoratively dismissed as “different therapies” now have a proven track record in specified areas of medicine, specifically the place brain impairment is concerned.


Art therapies and interventions are not resource neutral – not significantly is – but there are apparent bonuses. Offering psychological respite to a disturbed youngster or a dementia-stricken grownup by way of pleasure rather than pharmaceuticals has to be desirable wherever attainable.


Inducing calm or a sense of achievement in sufferers as an alternative of distress or aggravation is a much more than welcome outcome for carers and households, no less the daily victims of stress.


Art therapies have turn out to be a mainstream spouse to medicalised healing | Ruth Wishart

2 Ocak 2014 Perşembe

Bangladesh shipbuilder sets benchmark in overall health and safety standards | Ruth Evans

MDG : Western Marine Shipyards Ltd, one of Bangladesh’s leading shipyards

Bangladesh’s Western Marine Shipyards has witnessed a 99% reduction in accidents. Photograph: WMS


In a cavernous hangar, an imam recites a short prayer as employees gather round. When he has completed, managers sporting white overalls and hardhats mount the platform, pick up wooden mallets and strike an aluminium keel.


The noise ricochets close to Western Marine Shipyards, 1 of Bangladesh’s leading shipyards, as absolutely everyone applauds. The keel is the basis and spine of any ship, and this short keel-laying ceremony marks the begin of work on the shipyard’s most recent buy. Work also recommences on the 13 other ships, fishing trawlers and ferries in different stages of construction at the yard.


Shipbuilding is a development industry for the nation, bringing in considerably-essential foreign currency. Export earnings from ship development reached $ 46m in 2010-eleven and the government hopes the sector will contribute 4%-5 % of GDP by 2015 – and possibly develop 1m jobs.


3 years in the past, problems at this Chittagong shipyard had been extremely distinct, with one,000 injuries a month in a workforce of 3,500. Now, through reasonably basic measures, there has been a 99% reduction in accidents.


This has been attained by way of a public-private partnership among Western Marine and Deutsche Gesellschaft für Internationale Zusammenarbeit (GIZ) to promote better well being and security in the workplace. A 3-yr partnership, portion of bilateral German advancement co-operation in collaboration with the ministry of wellness and loved ones welfare, was the first of its kind in Bangladesh utilizing personal sector infrastructure for the provision of public wellness providers.


Garment worker Bangladesh A worker inspects a factory in Dhaka soon after a fire killed eight individuals final Might. Photograph: Andrew Biraj/Reuters


The aim was to make sure a match and healthy workforce, by way of better accessibility to wellness providers, and the business agreed to build a health clinic. The wellness ministry pays for a nurse, and the shipyard pays for a element-time physician – who also attends to the nearby community – and two paramedics, who are also obtainable to the regional community, in which numerous of the workers live.


Following a welder was electrocuted and died whilst functioning without having protective equipment, Western Marine set about analysing the hazards and hazards employees faced – such as eye injuries and harm to hearing from noise. A health and security policy was drawn up to tackle the higher accident charges, training was provided for managers and workers, and protective clothes and products have been distributed.


Rigid reporting procedures had been established, so that every single incident or accident was recorded and investigated, and preventive measures implemented. The shipyard also recruited a wellness and security adviser to monitor, record and deal with any important troubles. The influence of these measures was quick and dramatic.


Well being and safety is now embedded in the company’s practices. “The initial issue is that when you do any task you guarantee the security is assured for all the employees – that is the leading priority,” says Arifur Rahman Khan, the firm’s technical director, “Which is how we begin our day.” In the past 3 years there have been no fatal accidents.


As a result, the clinic can focus on typical health checks for employees, to determine perform-related problems. The underlying philosophy is that prevention is greater than cure . “If we look right after our people, we’ll get better perform from them,” says Abu Mohammed Fazle Rashid, the deputy managing director.


Kemal Hasan, a welder, says circumstances have improved enormously. Now, he constantly wears gloves, protective overalls and a face mask, which prevent a lot of the injuries that previously occurred. There are fewer stoppages due to accidents, he says, and morale has improved. Workers want to keep with the organization simply because conditions are greater than elsewhere.


Considering that the Rana Plaza garment factory collapsed in April, with the loss of a lot more than 1,100 lives and 2,500 employees injured, and fatalities in fires in other factories, international consumers are increasingly demanding better overall health and safety checks. There is also a developing recognition that health and security are not just a matter of worker’s rights, but also an essential improvement situation. One particular worker often supports a massive extended family members, so fatalities or injuries can be catastrophic for communities. A healthy and productive workforce is important for economic improvement, and employers have a vital role to play.


Bangladesh has come underneath intense worldwide strain to overhaul labour laws and working problems. Nevertheless, Dr Paul Rueckert, GIZ’s principal adviser for overall health in Bangladesh, believes as well much consideration has been targeted on reactive processes to deal with fire and development hazards alternatively of introducing a lot more extensive occupational health and safety programs. Impetus for change must come from the owners and managers of the sector, he says, not just be imposed by government inspectors, who are number of and can’t be all over the place at when.


Rueckert believes there has in no way been a stronger crucial for powerful occupational wellness and safety measures, and hopes the Marine Shipyards undertaking will turn into a model for other industries. The challenge will be to convince other employers in Bangladesh to stick to suit, and accept that workers’ health and safety should be a priority for each financial improvement and far better enterprise.


Bangladesh shipbuilder sets benchmark in overall health and safety standards | Ruth Evans